Post-Angioplasty Dissection Management: Bailout Strategies
After PTA, a dissection doesn't always mean immediate stenting. Learn the practical rules for managing femoro-popliteal dissections without turning a focal problem into a metal sentence.

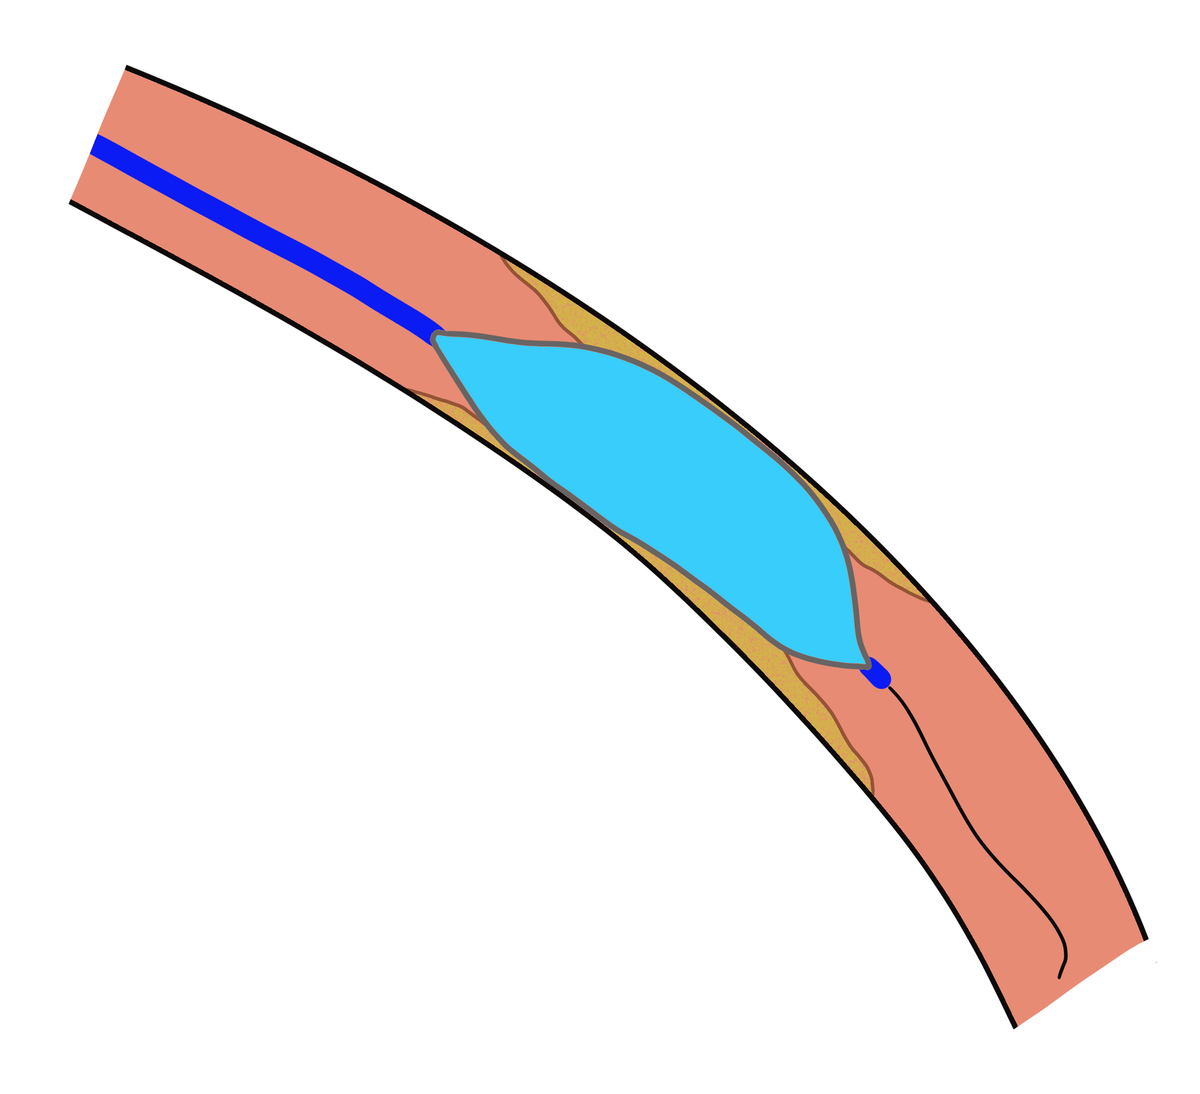
After PTA, a dissection doesn't always mean immediate stenting. Learn the practical rules for managing femoro-popliteal dissections without turning a focal problem into a metal sentence.
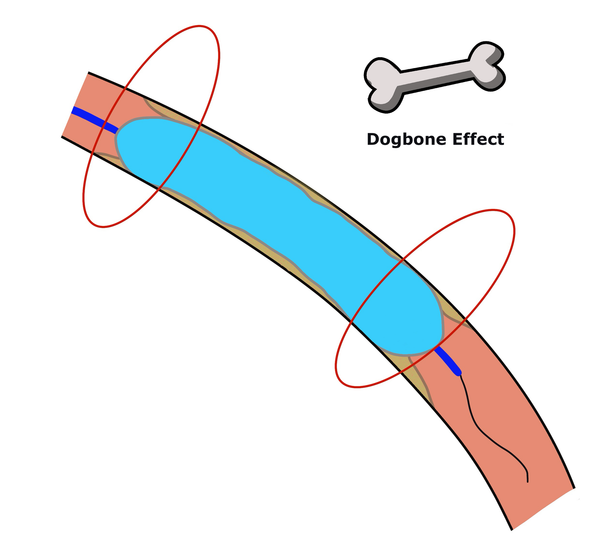
Before any dedicated device, two basic gestures already are vessel preparation: measuring the vessel correctly, and inflating very slowly up to nominal pressure — not beyond.
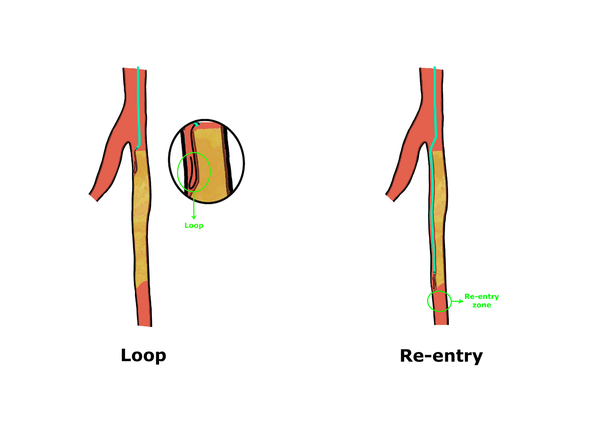
Once the decision is made to go subintimal, the technique becomes a matter of discipline: keeping the loop small, advancing the catheter behind the wire, and re-entering the true lumen right at the distal cap - the most demanding step of the entire procedure.
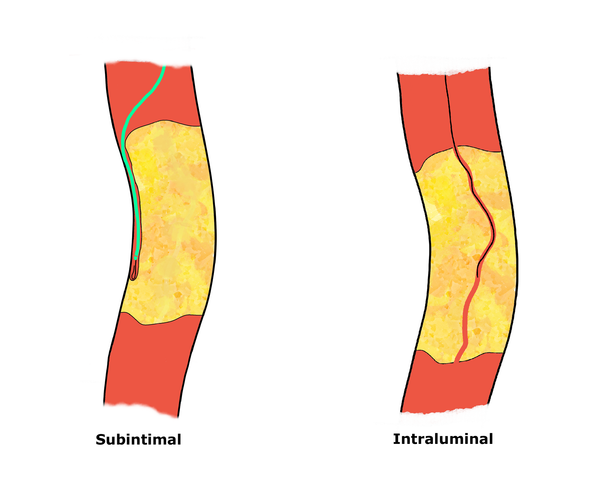
Once the Target Arterial Path is chosen, the technical question becomes how to cross the CTO. In long femoropopliteal occlusions the relationship between intraluminal and subintimal recanalization is more nuanced than the textbook sequence suggests — three scenarios worth distinguishing.
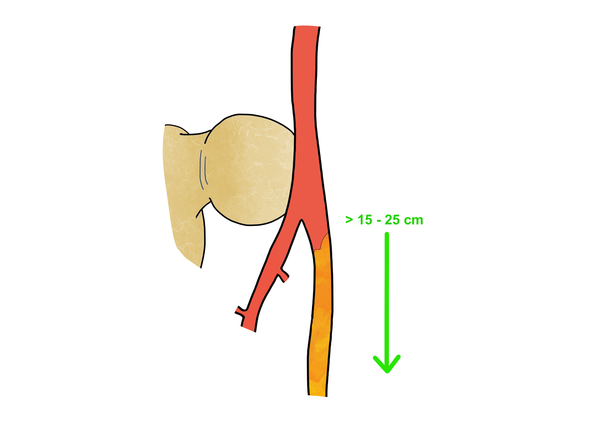
Before discussing how to cross a long or multilevel CTO, we need a more fundamental question: which vessel do we recanalize? The strategic framework of the 2019 Global Vascular Guidelines — Target Arterial Path, GLASS, and the role of the angiosome — defines everything that follows.